Introduction: Bladder cancer is one of the most common urological malignancies, with a high global incidence in men. Studies conducted in Dakar report a prevalence of 2.5% according to histopathological findings. Transurethral resection of the bladder (TURB) remains the cornerstone of treatment. The aim of this study was to describe the epidemiological, clinical, and therapeutic aspects of bladder cancer in urology departments in Ziguinchor. Methods: We conducted a retrospective, descriptive, and analytical study over five years (January 1, 2018 – December 31, 2023), including all bladder cancer cases managed in our departments. Patient data were collected from medical records. Chi-square (χ2) and Student’s t-tests were applied, with significance set at p < 0.05. Variables included epidemiological, clinical, paraclinical, TURB-related, therapeutic, and outcome data. Results: Bladder cancer was the second most frequent urological malignancy (22%), after prostate cancer (69%). The mean age of patients was 62.4 years with a male predominance 69.2% (n = 18). Median time for consultation was 60 days. Hematuria was reported in 88.5% (n = 23). General condition was poor Eastern Cooperative Oncology Group (ECOG3) in 58% of patients. Smoking was present in 34.6% (n = 9). Urinary tract ultrasound was performed in 84.6% (n = 22) and CT urography in 61.5% (n = 16). Cystoscopy and TURB were systematically performed, within an average of 3 months. Complications included hematuria and renal impairment. Urothelial carcinoma was found in 69.2% (n = 18). Total cystectomy was performed in 15.4% (n = 4). Overall, 50% (n = 13) of patients died. During follow-up, 15.4% (n = 4) were lost to follow-up at 3 months. Median survival was 4 months. Conclusion: Bladder cancer is prevalent among older adults. Cystoscopy was systematically performed in our study. TURB remains the cornerstone of treatment. Prognosis is poor at advanced stages.
This is an Open Access article, distributed under the terms of the Creative Commons Attribution 4.0 International License (http://creativecommons.org/licenses/by/4.0/), which permits unrestricted use, distribution and reproduction in any medium or format, provided the original work is properly cited.
Bladder cancer is among the most frequent malignancies of the urinary tract, with particularly high incidence in men worldwide
[1]
P Gontero, A Birtle, O Capoun, E Compérat, JL Dominguez-Escrig, F Liedberg, and al. European Association of Urology Guidelines on Non-muscle-invasive Bladder Cancer (TaT1 and Carcinoma In Situ) – A Summary of the 2024 Guidelines Update. Eur Urol 2024; 86: 531–49.
. In Africa, bladder cancer prevalence was estimated at 4% in 2018, with the highest mortality rate reported in Egypt in 2020, accounting for 7.8%
[3]
F Bray, J Ferlay, I Soerjomataram, RL Siegel, LA Torre, A Jemal. Global cancer statistics 2018: GLOBOCAN estimates of incidence and mortality worldwide for 36 cancers in 185 countries. CA Cancer J Clin 2018; 68: 394–424.
. Studies conducted in Dakar reported a prevalence of 2.5% of histologically confirmed cases
[5]
B Diao, T Amath, B Fall, PA Fall, MJ Diémé, NN Steevy, and al. Bladder cancers in Senegal: epidemiological, clinical, and histological characteristics. Prog Urol 2008; 18: 445–8.
M Traore, M Jalloh, M Yevi, M Ndoye, I Labou, L Niang, and al. Transurethral resection of bladder tumors at the Grand Yoff General Hospital: about 141 cases. Uro’Andro 2018; 1: 463–7.
[6, 7]
. Transurethral resection of the bladder (TURB) represents the cornerstone for diagnostic, prognostic, and therapeutic purposes
[2]
M Rouprêt. French recommendations from the AFU oncology committee – update 2022–2024. Prog Urol 2022; 32: 1009.
S Larré, P Leon, A El Bakri. Bladder cancer: diagnosis and treatment principles. EMC - Urol 2016; 9: 1–17.
[2, 8]
. This study aimed to describe the epidemiological, clinical, and therapeutic aspects of bladder cancer in the urology departments of Ziguinchor, Senegal.
2. Patients and Methods
We conducted a retrospective, descriptive, and analytical multicenter study over five years (January 1, 2018 – December 31, 2023), including all cases of bladder cancer managed at the Regional Hospital and peace hospital of Ziguinchor. Data were collected from patient medical records. Statistical analysis included Pearson’s Chi-square (χ2) and Student’s t-tests, with significance set at p < 0.05.
TURB: time, duration of intervention, bladder irrigation, duration of catheterization, histological type, tumor stage (TNM classification), postoperative laboratory follow-up.
Therapeutic: curative or palliative, immediate postoperative outcomes, length of hospitalization, morbidity and mortality.
3. Results
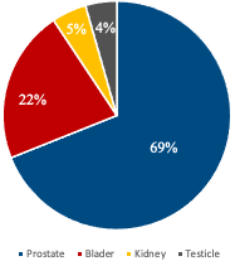
Twenty-six cases of bladder cancer were included, representing the second most frequent urological malignancy (22%), after prostate cancer (69%) (Figure 1). The mean age was 62.4 ± 12 years [38–84], with the age group of [60–80] the most represented (46.2%) and a male predominance 69.2% (n = 18) ; sex ratio 2.3). Regarding occupation, farmers represented the majority 19.9% (n = 5).
Figure 1. Distribution of urological cancers by location.
Median consultation time was 60 days [9–730], with 69.2% of patients presented within the first 3 months. Macroscopic hematuria was the most frequent reported symptom 88.5% (n = 23) (Table 1). Poor general condition (ECOG 3) was observed in 58%. Smoking was the main risk factor 34.6% (n = 9), and one case of urinary schistosomiasis was confirmed.
Table 1. Distribution of patients according to circumstances of discovery.
Clinical Signs
Frequency
Percentage (%)
Hematuria
23
88,5
LUTS
21
80,8
Low Abdominal pain
13
50
Low Abdominal mass
9
34,6
Urinary retention
1
3,8
Mean hemoglobin levels was 10.1 g/dL [6.1–14.1]. Anemia was observed in 70% of cases, of which 47.8% required blood transfusion. Renal impairment was found in 38.5% (n = 10) of cases. Urine cytobacteriological examination revealed urinary tract infection in 50% (n = 13), most commonly caused by Esterichia coli (46.2%). Urinary cytology, performed in two patients, did not detect malignant cells.
Ultrasound of the urinary tract, performed in 84.6% (n = 22) of cases, identified tumors within the bladder in 73% of cases and ureterohydronephrosis in 61.5%. CT urography, performed in 61.5% (n = 16) of patients, revealed ureteral invasion in 15.8% (n = 4) and ureterohydronephrosis in 46.1% (n = 12).
Cystoscopy, performed in all patients, showed a single tumor in 80% (n = 21), sessile in 92.3% (n = 24), and exophytic in 88.5% (n = 23) of patients. The tumor involved the ureteral orifice in 76.9% (n = 20) and the trigone in 26.9% of cases.
TURB was performed in all patients within a mean delay of 3 months; of whom 69.2% underwent the procedure within this period. Spinal anesthesia was used in 84.6% of cases. Mean resection duration was 53.1 min [30–100]. Mean bladder irrigation was 2 days [1–12], and catheter duration averaged 4 days [2–14]. Mean hospital stay was 4.6 days [1–15], with ≤3 days in 59% (n = 15).
After resection, renal impairment was observed in 38.5% (n = 7) of cases and mean hemoglobin was 9.7 g/dL [8.2–13.3], without significant difference from baseline (p = 0.95). Hematuria occurred in 19.2% (n = 5) and was the early complication. It was corrected by transfusion, while one patient required readmission to the operating room.
Urothelial carcinoma was more frequent, accounting for 69.2% (n = 18), followed by squamous cell carcinoma at 23% (n = 7). The tumor was non-invasive in 19.2% (n = 5) and predominantly high grade in 92.3% (n = 24). It was localized in 38.5% (n = 10) of cases (Table 2). Localized tumors (70%) were associated with poor general condition (ECOG3), whereas all cases of locoregional stage had a general condition of ECOG2, without significant difference (p = 0.05). One patient underwent a second-look TURB for muscle-invasive pT1 urothelial carcinoma. Neoadjuvant chemotherapy was performed in one patient. Radical cystectomy was performed in 15.4% (n = 4), including two cystoprostatectomies and two anterior pelvic exenterations with Bricker diversion. Palliative chemotherapy (MVAC) and Bricker diversion were performed in one patient each with metastatic squamous cell carcinoma.
Table 2. Distribution of patients according to TNM stage.
TNM Stage
Frequency
Percentage (%)
Localized MIBC
10
38.5
NMIBC
6
25
Metastatic MIBC
6
25
Locally advanced MIBC
4
15.5
Total
26
100
Among patients with muscle-invasive tumors, 65% (n = 13) were lost to follow-up or died before treatment. Mean length of hospital stay was 9 days for cystoprostatectomy and 8 days for anterior pelvic exenteration. Complications included stoma infection, deep vein thrombosis, and deteriorated general condition in 38.5% (n = 7), requiring antibiotics, anticoagulation, nutritional support, and transfusion. Overall, death occurred in 50% (n = 13) of patients (Table 3).
Table 3. Distribution of patients according to prognosis.
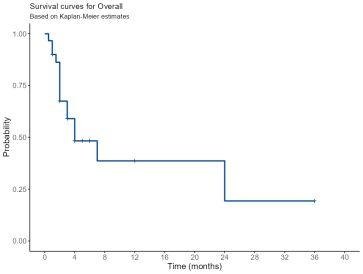
Loss to follow-up was 11.5% (n = 3) at 3 months and 15.4% (n = 4) at 6 months. Median overall survival was 4 months (Figure 2).
4. Discussion
In our series, bladder cancer was the second most common urological malignancy, following prostate cancer. This ranking was also reported by B Diao and al.
[5]
B Diao, T Amath, B Fall, PA Fall, MJ Diémé, NN Steevy, and al. Bladder cancers in Senegal: epidemiological, clinical, and histological characteristics. Prog Urol 2008; 18: 445–8.
. The higher exposure of men to risk factors such as smoking and schistosomiasis may explain the male predominance observed, a pattern also reported in other studies
[5]
B Diao, T Amath, B Fall, PA Fall, MJ Diémé, NN Steevy, and al. Bladder cancers in Senegal: epidemiological, clinical, and histological characteristics. Prog Urol 2008; 18: 445–8.
M Traore, M Jalloh, M Yevi, M Ndoye, I Labou, L Niang, and al. Transurethral resection of bladder tumors at the Grand Yoff General Hospital: about 141 cases. Uro’Andro 2018; 1: 463–7.
[8]
S Larré, P Leon, A El Bakri. Bladder cancer: diagnosis and treatment principles. EMC - Urol 2016; 9: 1–17.
[5, 7, 8]
. Smoking is the main risk factor for urothelial carcinoma of the bladder and was present in more than half of our patients. Indeed, smokers have a 2.5-fold increased risk of developing bladder cancer
[9]
J Mushtaq, R Thurairaja, R Nair. Bladder cancer. Surgery (Oxford) 2019; 37: 529–37.
. Farmers were the predominant occupational group in our series. Studies have shown that exposure to pesticides is associated with an increased risk of bladder cancer
[10]
NF Abbas, MR Aoude, HR Kourie, HO Al-Shamsi. Uncovering the epidemiology of bladder cancer in the Arab world: a review of risk factors, molecular mechanisms, and clinical features. Asian J Urol 2024; 11: 406–22.
The mean consultation time in our study was 4 months. MT Traoré and al, reported a mean time of 7 months [range: 1–22 months]
[7]
M Traore, M Jalloh, M Yevi, M Ndoye, I Labou, L Niang, and al. Transurethral resection of bladder tumors at the Grand Yoff General Hospital: about 141 cases. Uro’Andro 2018; 1: 463–7.
[7]
. This diagnostic delay may be explained by cultural normalization of early symptoms. Total hematuria was observed in nearly all patients, which corroborates findings from previous authors, confirming that hematuria is the main presenting sign of bladder tumors
[8]
S Larré, P Leon, A El Bakri. Bladder cancer: diagnosis and treatment principles. EMC - Urol 2016; 9: 1–17.
[11]
R Salah, N Harir, S Zeggai, F Sellam, NM Merabent, S Moullessehoul, and al. Urological cancers in Algeria: histo-epidemiological profile of 348 cases. J Afr Cancer 2015; 7: 126–31.
M Sow, B Nkégoum, J-LE Oyono, N Garoua, A Nzokou. Epidemiological and histological features of urogenital tumors in Cameroon. Prog Urol 2006; 16: 36–9.
[8, 11, 12]
.
Anemia was observed in more than half of the patients, reflecting the hemorrhagic nature of bladder tumors. Renal impairment was also noted, and preoperative correction of these disorders may reduce the risk of early postoperative complications
[13]
R Mastroianni, G Tuderti, M Ferriero, U Anceschi, AM Bove, A Brassetti, and al. Robot-assisted radical cystectomy with totally intracorporeal urinary diversion versus open radical cystectomy: 3-year outcomes from a randomized controlled trial. Eur Urol 2024; 85: 422–30.
. In our study, urinary tract ultrasonography was widely performed and contributed to both diagnosis and assessment of tumor impact. MT Traoré and al, reported bladder wall thickening in 40.7% and upper urinary tract involvement in nearly 65% of patients
[7]
M Traore, M Jalloh, M Yevi, M Ndoye, I Labou, L Niang, and al. Transurethral resection of bladder tumors at the Grand Yoff General Hospital: about 141 cases. Uro’Andro 2018; 1: 463–7.
[7]
. In the literature, ultrasound sensitivity for polypoid tumors larger than 5 mm ranges from 61% to 84%
[8]
S Larré, P Leon, A El Bakri. Bladder cancer: diagnosis and treatment principles. EMC - Urol 2016; 9: 1–17.
[8]
.
CT urography was performed in the majority of patients and aided in diagnosis and assessment of tumor extension. Cystoscopy, performed in all patients, remained the cornerstone for positive diagnosis. O Gaye and al.
[15]
O Gaye, M Jalloh, M Ndoye, A Tall, NM Thiam, C Dial, and al. Bladder cancer in Senegal: what’s new? African Urology 2023; 3: 14–8.
performed cystoscopy in 83.7% of cases, of which 55.8% were unifocal; I Diallo and al.
[16]
I Diallo, I Diamé, C Diouf, S Faye, A Thiam, A Yaya, and al. Urogenital cancers in peripheral regions of Senegal: a study of 156 cases. African Journal of Urology 2021; 27: 9–16.
reported 100% detection by cystoscopy, with 41.2% being unilateral.
TURB has both diagnostic and therapeutic roles and should be as complete as possible. Visualization can be enhanced by hexaminolevulinate injection to better detect flat lesions. The long delay before TURB may be explained by financial constraints and reliance on traditional medicine in our region. Resection was sometimes incomplete, reflecting the large size of tumors in our series. Early hemorrhagic complications were noted intra- and postoperatively, requiring blood transfusions or reoperation for electrocoagulation and clot removal. No bladder perforation was observed in our series; the literature reports intraoperative perforation rates ranging from 1.3% to 4%
[17]
A Collado, GE Chéchile, J Salvador, J Vicente. Early complications of endoscopic treatment for superficial bladder tumors. J Urol 2000; 164: 1529–32.
A Pycha, M Lodde, L Lusuardi, S Palermo, D Signorello, A Galantini, and al. Teaching transurethral resection of the bladder: still a challenge? Urology 2003; 62: 46–8.
Urothelial carcinoma was the most frequent histological type, followed by squamous cell carcinoma. I Diallo and al, reported urothelial carcinoma in 95.7% and squamous cell carcinoma in 1.4% of cases
[16]
I Diallo, I Diamé, C Diouf, S Faye, A Thiam, A Yaya, and al. Urogenital cancers in peripheral regions of Senegal: a study of 156 cases. African Journal of Urology 2021; 27: 9–16.
. This trend may be explained, in one hand by the effectiveness of urogenital schistosomiasis control programs and, on the other hand, by increased urbanization, industrialization, and smoking in many African countries
[19]
F-I Hsieh, T-S Hwang, Y-C Hsieh, H-C Lo, C-T Su, H-S Hsu, and al. Risk of erectile dysfunction induced by arsenic exposure through well water consumption in Taiwan. Environ Health Perspect 2008; 116: 532–6.
. Most of our patients had invasive and metastatic tumors. I Diallo and al.
[16]
I Diallo, I Diamé, C Diouf, S Faye, A Thiam, A Yaya, and al. Urogenital cancers in peripheral regions of Senegal: a study of 156 cases. African Journal of Urology 2021; 27: 9–16.
reported 70% invasive tumors, while the literature reports rates between 15% and 25%
[8]
S Larré, P Leon, A El Bakri. Bladder cancer: diagnosis and treatment principles. EMC - Urol 2016; 9: 1–17.
[8]
.
For the majority of non-muscle-invasive bladder tumors (NMIBCs) in our series, TURB was the sole therapeutic approach. Early postoperative intravesical instillations (mitomycin C) or immunotherapy (BCG) are recommended for non-invasive tumors, which reduce recurrence risk from 35% at 1 year to 14% at 5 years
[2]
M Rouprêt. French recommendations from the AFU oncology committee – update 2022–2024. Prog Urol 2022; 32: 1009.
. No patient in our series received these adjunct therapies due to unavailability. Radical surgery was indicated in four patients with non-metastatic muscle-invasive bladder tumors, in accordance with AFU recommendations
[2]
M Rouprêt. French recommendations from the AFU oncology committee – update 2022–2024. Prog Urol 2022; 32: 1009.
S Larré, P Leon, A El Bakri. Bladder cancer: diagnosis and treatment principles. EMC - Urol 2016; 9: 1–17.
[2, 8]
.
Neoadjuvant chemotherapy was performed in one patient, and palliative chemotherapy (MVAC) in one patient with metastatic squamous cell carcinoma. The efficacy of neoadjuvant chemotherapy for muscle-invasive bladder tumors has been demonstrated in randomized trials and shows similar benefit in the adjuvant setting
[20]
CN Sternberg, I Skoneczna, JM Kerst, P Albers, SD Fossa, M Agerbaek, and al. Immediate versus deferred chemotherapy after radical cystectomy in patients with pT3-pT4 or N+ M0 urothelial carcinoma of the bladder (EORTC 30994): an intergroup, open-label, randomized phase 3 trial. Lancet Oncol 2015; 16: 76–86.
. Median survival in our study was 4 months. The literature reports median survival of 3–6 months in untreated metastatic patients
[8]
S Larré, P Leon, A El Bakri. Bladder cancer: diagnosis and treatment principles. EMC - Urol 2016; 9: 1–17.
[8]
. This poor survival may be explained by advanced disease at diagnosis and the unavailability of immunotherapy and neoadjuvant chemotherapy in our centers.
5. Conclusion
Bladder cancer is highly prevalent among older adults. Smoking is the main risk factor. Hematuria is the primary symptom, and imaging, particularly cystoscopy, is essential for diagnosis. TURB remains the cornerstone of treatment and may be combined with systemic therapy. Prognosis remains poor among patients diagnosed at advanced stages.
Abbreviations
TURB
Transurethral Resection of the Bladder
ECOG3
Eastern Cooperative Oncology Group
MVAC
Methotrexate Vinblastine Adriamycin Cisplatin
AFU
French Associationof Urology
Conflicts of Interest
The authors declare no conflicts of interest.
References
[1]
P Gontero, A Birtle, O Capoun, E Compérat, JL Dominguez-Escrig, F Liedberg, and al. European Association of Urology Guidelines on Non-muscle-invasive Bladder Cancer (TaT1 and Carcinoma In Situ) – A Summary of the 2024 Guidelines Update. Eur Urol 2024; 86: 531–49.
F Bray, J Ferlay, I Soerjomataram, RL Siegel, LA Torre, A Jemal. Global cancer statistics 2018: GLOBOCAN estimates of incidence and mortality worldwide for 36 cancers in 185 countries. CA Cancer J Clin 2018; 68: 394–424.
B Diao, T Amath, B Fall, PA Fall, MJ Diémé, NN Steevy, and al. Bladder cancers in Senegal: epidemiological, clinical, and histological characteristics. Prog Urol 2008; 18: 445–8.
M Traore, M Jalloh, M Yevi, M Ndoye, I Labou, L Niang, and al. Transurethral resection of bladder tumors at the Grand Yoff General Hospital: about 141 cases. Uro’Andro 2018; 1: 463–7.
[8]
S Larré, P Leon, A El Bakri. Bladder cancer: diagnosis and treatment principles. EMC - Urol 2016; 9: 1–17.
[9]
J Mushtaq, R Thurairaja, R Nair. Bladder cancer. Surgery (Oxford) 2019; 37: 529–37.
NF Abbas, MR Aoude, HR Kourie, HO Al-Shamsi. Uncovering the epidemiology of bladder cancer in the Arab world: a review of risk factors, molecular mechanisms, and clinical features. Asian J Urol 2024; 11: 406–22.
R Salah, N Harir, S Zeggai, F Sellam, NM Merabent, S Moullessehoul, and al. Urological cancers in Algeria: histo-epidemiological profile of 348 cases. J Afr Cancer 2015; 7: 126–31.
M Sow, B Nkégoum, J-LE Oyono, N Garoua, A Nzokou. Epidemiological and histological features of urogenital tumors in Cameroon. Prog Urol 2006; 16: 36–9.
[13]
R Mastroianni, G Tuderti, M Ferriero, U Anceschi, AM Bove, A Brassetti, and al. Robot-assisted radical cystectomy with totally intracorporeal urinary diversion versus open radical cystectomy: 3-year outcomes from a randomized controlled trial. Eur Urol 2024; 85: 422–30.
I Diallo, I Diamé, C Diouf, S Faye, A Thiam, A Yaya, and al. Urogenital cancers in peripheral regions of Senegal: a study of 156 cases. African Journal of Urology 2021; 27: 9–16.
A Pycha, M Lodde, L Lusuardi, S Palermo, D Signorello, A Galantini, and al. Teaching transurethral resection of the bladder: still a challenge? Urology 2003; 62: 46–8.
F-I Hsieh, T-S Hwang, Y-C Hsieh, H-C Lo, C-T Su, H-S Hsu, and al. Risk of erectile dysfunction induced by arsenic exposure through well water consumption in Taiwan. Environ Health Perspect 2008; 116: 532–6.
CN Sternberg, I Skoneczna, JM Kerst, P Albers, SD Fossa, M Agerbaek, and al. Immediate versus deferred chemotherapy after radical cystectomy in patients with pT3-pT4 or N+ M0 urothelial carcinoma of the bladder (EORTC 30994): an intergroup, open-label, randomized phase 3 trial. Lancet Oncol 2015; 16: 76–86.
Traore, A., Ndiaye, M. D., Diouf, M., Diallo, I., Doukoure, M., et al. (2025). Bladder Cancer: Epidemiological, Clinical, and Therapeutic Aspects in Hospitals of Ziguinchor City. International Journal of Clinical Urology, 9(2), 204-208. https://doi.org/10.11648/j.ijcu.20250902.27
Traore, A.; Ndiaye, M. D.; Diouf, M.; Diallo, I.; Doukoure, M., et al. Bladder Cancer: Epidemiological, Clinical, and Therapeutic Aspects in Hospitals of Ziguinchor City. Int. J. Clin. Urol.2025, 9(2), 204-208. doi: 10.11648/j.ijcu.20250902.27
Traore A, Ndiaye MD, Diouf M, Diallo I, Doukoure M, et al. Bladder Cancer: Epidemiological, Clinical, and Therapeutic Aspects in Hospitals of Ziguinchor City. Int J Clin Urol. 2025;9(2):204-208. doi: 10.11648/j.ijcu.20250902.27
@article{10.11648/j.ijcu.20250902.27,
  author = {Aboubacar Traore and Modou Diop Ndiaye and Massaer Diouf and Ibrahima Diallo and Mohamed Doukoure and Omar Sow and Boubacar Fall},
  title = {Bladder Cancer: Epidemiological, Clinical, and Therapeutic Aspects in Hospitals of Ziguinchor City},
  journal = {International Journal of Clinical Urology},
  volume = {9},
  number = {2},
  pages = {204-208},
  doi = {10.11648/j.ijcu.20250902.27},
  url = {https://doi.org/10.11648/j.ijcu.20250902.27},
  eprint = {https://article.sciencepublishinggroup.com/pdf/10.11648.j.ijcu.20250902.27},
  abstract = {Introduction: Bladder cancer is one of the most common urological malignancies, with a high global incidence in men. Studies conducted in Dakar report a prevalence of 2.5% according to histopathological findings. Transurethral resection of the bladder (TURB) remains the cornerstone of treatment. The aim of this study was to describe the epidemiological, clinical, and therapeutic aspects of bladder cancer in urology departments in Ziguinchor. Methods: We conducted a retrospective, descriptive, and analytical study over five years (January 1, 2018 – December 31, 2023), including all bladder cancer cases managed in our departments. Patient data were collected from medical records. Chi-square (χ2) and Student’s t-tests were applied, with significance set at p < 0.05. Variables included epidemiological, clinical, paraclinical, TURB-related, therapeutic, and outcome data. Results: Bladder cancer was the second most frequent urological malignancy (22%), after prostate cancer (69%). The mean age of patients was 62.4 years with a male predominance 69.2% (n = 18). Median time for consultation was 60 days. Hematuria was reported in 88.5% (n = 23). General condition was poor Eastern Cooperative Oncology Group (ECOG3) in 58% of patients. Smoking was present in 34.6% (n = 9). Urinary tract ultrasound was performed in 84.6% (n = 22) and CT urography in 61.5% (n = 16). Cystoscopy and TURB were systematically performed, within an average of 3 months. Complications included hematuria and renal impairment. Urothelial carcinoma was found in 69.2% (n = 18). Total cystectomy was performed in 15.4% (n = 4). Overall, 50% (n = 13) of patients died. During follow-up, 15.4% (n = 4) were lost to follow-up at 3 months. Median survival was 4 months. Conclusion: Bladder cancer is prevalent among older adults. Cystoscopy was systematically performed in our study. TURB remains the cornerstone of treatment. Prognosis is poor at advanced stages.},
 year = {2025}
}
TY  - JOUR
T1  - Bladder Cancer: Epidemiological, Clinical, and Therapeutic Aspects in Hospitals of Ziguinchor City
AU  - Aboubacar Traore
AU  - Modou Diop Ndiaye
AU  - Massaer Diouf
AU  - Ibrahima Diallo
AU  - Mohamed Doukoure
AU  - Omar Sow
AU  - Boubacar Fall
Y1  - 2025/12/26
PY  - 2025
N1  - https://doi.org/10.11648/j.ijcu.20250902.27
DO  - 10.11648/j.ijcu.20250902.27
T2  - International Journal of Clinical Urology
JF  - International Journal of Clinical Urology
JO  - International Journal of Clinical Urology
SP  - 204
EP  - 208
PB  - Science Publishing Group
SN  - 2640-1355
UR  - https://doi.org/10.11648/j.ijcu.20250902.27
AB  - Introduction: Bladder cancer is one of the most common urological malignancies, with a high global incidence in men. Studies conducted in Dakar report a prevalence of 2.5% according to histopathological findings. Transurethral resection of the bladder (TURB) remains the cornerstone of treatment. The aim of this study was to describe the epidemiological, clinical, and therapeutic aspects of bladder cancer in urology departments in Ziguinchor. Methods: We conducted a retrospective, descriptive, and analytical study over five years (January 1, 2018 – December 31, 2023), including all bladder cancer cases managed in our departments. Patient data were collected from medical records. Chi-square (χ2) and Student’s t-tests were applied, with significance set at p < 0.05. Variables included epidemiological, clinical, paraclinical, TURB-related, therapeutic, and outcome data. Results: Bladder cancer was the second most frequent urological malignancy (22%), after prostate cancer (69%). The mean age of patients was 62.4 years with a male predominance 69.2% (n = 18). Median time for consultation was 60 days. Hematuria was reported in 88.5% (n = 23). General condition was poor Eastern Cooperative Oncology Group (ECOG3) in 58% of patients. Smoking was present in 34.6% (n = 9). Urinary tract ultrasound was performed in 84.6% (n = 22) and CT urography in 61.5% (n = 16). Cystoscopy and TURB were systematically performed, within an average of 3 months. Complications included hematuria and renal impairment. Urothelial carcinoma was found in 69.2% (n = 18). Total cystectomy was performed in 15.4% (n = 4). Overall, 50% (n = 13) of patients died. During follow-up, 15.4% (n = 4) were lost to follow-up at 3 months. Median survival was 4 months. Conclusion: Bladder cancer is prevalent among older adults. Cystoscopy was systematically performed in our study. TURB remains the cornerstone of treatment. Prognosis is poor at advanced stages.
VL  - 9
IS  - 2
ER  -
Traore, A., Ndiaye, M. D., Diouf, M., Diallo, I., Doukoure, M., et al. (2025). Bladder Cancer: Epidemiological, Clinical, and Therapeutic Aspects in Hospitals of Ziguinchor City. International Journal of Clinical Urology, 9(2), 204-208. https://doi.org/10.11648/j.ijcu.20250902.27
Traore, A.; Ndiaye, M. D.; Diouf, M.; Diallo, I.; Doukoure, M., et al. Bladder Cancer: Epidemiological, Clinical, and Therapeutic Aspects in Hospitals of Ziguinchor City. Int. J. Clin. Urol.2025, 9(2), 204-208. doi: 10.11648/j.ijcu.20250902.27
Traore A, Ndiaye MD, Diouf M, Diallo I, Doukoure M, et al. Bladder Cancer: Epidemiological, Clinical, and Therapeutic Aspects in Hospitals of Ziguinchor City. Int J Clin Urol. 2025;9(2):204-208. doi: 10.11648/j.ijcu.20250902.27
@article{10.11648/j.ijcu.20250902.27,
  author = {Aboubacar Traore and Modou Diop Ndiaye and Massaer Diouf and Ibrahima Diallo and Mohamed Doukoure and Omar Sow and Boubacar Fall},
  title = {Bladder Cancer: Epidemiological, Clinical, and Therapeutic Aspects in Hospitals of Ziguinchor City},
  journal = {International Journal of Clinical Urology},
  volume = {9},
  number = {2},
  pages = {204-208},
  doi = {10.11648/j.ijcu.20250902.27},
  url = {https://doi.org/10.11648/j.ijcu.20250902.27},
  eprint = {https://article.sciencepublishinggroup.com/pdf/10.11648.j.ijcu.20250902.27},
  abstract = {Introduction: Bladder cancer is one of the most common urological malignancies, with a high global incidence in men. Studies conducted in Dakar report a prevalence of 2.5% according to histopathological findings. Transurethral resection of the bladder (TURB) remains the cornerstone of treatment. The aim of this study was to describe the epidemiological, clinical, and therapeutic aspects of bladder cancer in urology departments in Ziguinchor. Methods: We conducted a retrospective, descriptive, and analytical study over five years (January 1, 2018 – December 31, 2023), including all bladder cancer cases managed in our departments. Patient data were collected from medical records. Chi-square (χ2) and Student’s t-tests were applied, with significance set at p < 0.05. Variables included epidemiological, clinical, paraclinical, TURB-related, therapeutic, and outcome data. Results: Bladder cancer was the second most frequent urological malignancy (22%), after prostate cancer (69%). The mean age of patients was 62.4 years with a male predominance 69.2% (n = 18). Median time for consultation was 60 days. Hematuria was reported in 88.5% (n = 23). General condition was poor Eastern Cooperative Oncology Group (ECOG3) in 58% of patients. Smoking was present in 34.6% (n = 9). Urinary tract ultrasound was performed in 84.6% (n = 22) and CT urography in 61.5% (n = 16). Cystoscopy and TURB were systematically performed, within an average of 3 months. Complications included hematuria and renal impairment. Urothelial carcinoma was found in 69.2% (n = 18). Total cystectomy was performed in 15.4% (n = 4). Overall, 50% (n = 13) of patients died. During follow-up, 15.4% (n = 4) were lost to follow-up at 3 months. Median survival was 4 months. Conclusion: Bladder cancer is prevalent among older adults. Cystoscopy was systematically performed in our study. TURB remains the cornerstone of treatment. Prognosis is poor at advanced stages.},
 year = {2025}
}
TY  - JOUR
T1  - Bladder Cancer: Epidemiological, Clinical, and Therapeutic Aspects in Hospitals of Ziguinchor City
AU  - Aboubacar Traore
AU  - Modou Diop Ndiaye
AU  - Massaer Diouf
AU  - Ibrahima Diallo
AU  - Mohamed Doukoure
AU  - Omar Sow
AU  - Boubacar Fall
Y1  - 2025/12/26
PY  - 2025
N1  - https://doi.org/10.11648/j.ijcu.20250902.27
DO  - 10.11648/j.ijcu.20250902.27
T2  - International Journal of Clinical Urology
JF  - International Journal of Clinical Urology
JO  - International Journal of Clinical Urology
SP  - 204
EP  - 208
PB  - Science Publishing Group
SN  - 2640-1355
UR  - https://doi.org/10.11648/j.ijcu.20250902.27
AB  - Introduction: Bladder cancer is one of the most common urological malignancies, with a high global incidence in men. Studies conducted in Dakar report a prevalence of 2.5% according to histopathological findings. Transurethral resection of the bladder (TURB) remains the cornerstone of treatment. The aim of this study was to describe the epidemiological, clinical, and therapeutic aspects of bladder cancer in urology departments in Ziguinchor. Methods: We conducted a retrospective, descriptive, and analytical study over five years (January 1, 2018 – December 31, 2023), including all bladder cancer cases managed in our departments. Patient data were collected from medical records. Chi-square (χ2) and Student’s t-tests were applied, with significance set at p < 0.05. Variables included epidemiological, clinical, paraclinical, TURB-related, therapeutic, and outcome data. Results: Bladder cancer was the second most frequent urological malignancy (22%), after prostate cancer (69%). The mean age of patients was 62.4 years with a male predominance 69.2% (n = 18). Median time for consultation was 60 days. Hematuria was reported in 88.5% (n = 23). General condition was poor Eastern Cooperative Oncology Group (ECOG3) in 58% of patients. Smoking was present in 34.6% (n = 9). Urinary tract ultrasound was performed in 84.6% (n = 22) and CT urography in 61.5% (n = 16). Cystoscopy and TURB were systematically performed, within an average of 3 months. Complications included hematuria and renal impairment. Urothelial carcinoma was found in 69.2% (n = 18). Total cystectomy was performed in 15.4% (n = 4). Overall, 50% (n = 13) of patients died. During follow-up, 15.4% (n = 4) were lost to follow-up at 3 months. Median survival was 4 months. Conclusion: Bladder cancer is prevalent among older adults. Cystoscopy was systematically performed in our study. TURB remains the cornerstone of treatment. Prognosis is poor at advanced stages.
VL  - 9
IS  - 2
ER  -





 Share This Article
 Twitter
 Linked In
 Facebook

 Copy
 Download